

An Ambetter appeal letter only works if it goes down the right route. Payment, coding and timely filing denials go through Ambetter's provider Request for Reconsideration (Level I) and then Claim Dispute (Level II). The Level II dispute must be filed on Ambetter's claim dispute form, so your letter goes with the form as an attachment. In Ambetter's 2026 Kansas and Texas provider manuals, medical necessity and authorization denials go through the member appeal process instead. The member has 180 calendar days to appeal, and the provider can file for the member, though written consent may be required. Provider deadlines differ by state: 90 days in Florida, 120 in Texas and 180 in Kansas, based on the 2026 manuals. The four templates below cover each route.
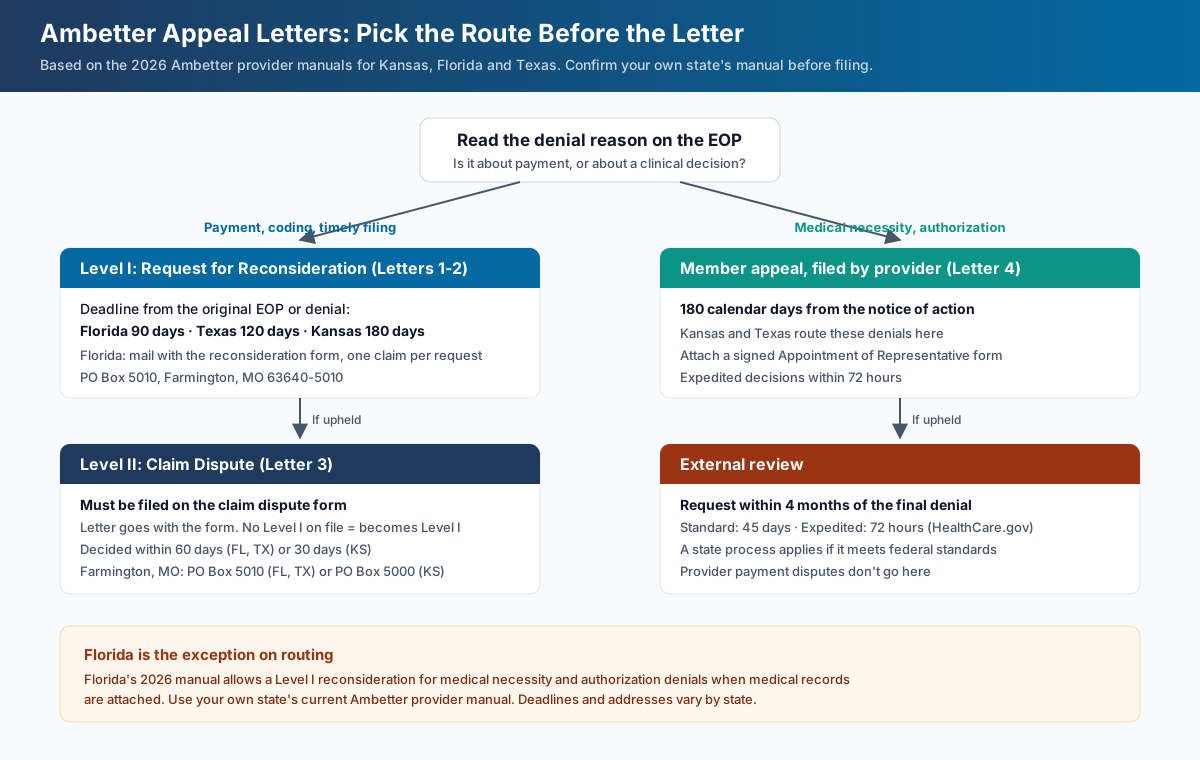
Which Ambetter Appeal Letter Do You Need?
Choose the letter from the denial reason on the Explanation of Payment (EOP), not from how urgent the claim feels. Ambetter keeps provider payment disputes and member appeals of clinical decisions in separate queues, with separate addresses, and each queue has its own deadline.
The 2026 manuals for Ambetter from Sunflower Health Plan (Kansas) and Ambetter from Superior HealthPlan (Texas) both say medical necessity and authorization denials are "handled through the Member Appeal process". The 2026 Florida manual is different. It allows a Level I reconsideration for a medical necessity or authorization-related denial, as long as medical records are attached. The routing depends on the state, so check your state's manual before you pick a letter.
| Denial on the EOP | Ambetter route | Letter below | Sent to (2026 KS/FL/TX manuals) |
|---|---|---|---|
| Underpaid, wrong rate, bundling or code edit | Level I Request for Reconsideration | Letter 1 | Attn: Request for Reconsideration, PO Box 5010, Farmington, MO 63640-5010, or the Secure Provider Portal where your state allows it |
| Denied as untimely, but you filed on time | Level I Request for Reconsideration | Letter 2 | Same Level I address or portal |
| Level I upheld and you still disagree | Level II Claim Dispute (on the dispute form) | Letter 3 | Attn: Claim Dispute, Farmington, MO (PO Box 5010 in FL and TX, PO Box 5000 in KS) |
| Medical necessity or prior authorization denial | Member appeal filed by the provider for the member (KS and TX), or Level I with records (FL) | Letter 4 | The Appeals and Grievances address on the denial notice |
A claim that needs changes is not a reconsideration
If the claim itself was wrong (a missing modifier, a wrong code or a wrong date), send a corrected claim with frequency code 7 instead of an appeal letter. Florida's form tells providers not to include the dispute form with a corrected claim. See corrected claim vs. insurance appeal for help deciding.
Ambetter Appeal Deadlines by State (2026 Provider Manuals)
Ambetter doesn't have one national provider appeal deadline. Kansas, Florida and Texas each set a different Level I window in their 2026 manuals, and each manual counts from the date of the original EOP or denial.
| Ambetter plan (2026 manual) | Level I reconsideration | Level II claim dispute | Dispute decision | How Level I can be sent |
|---|---|---|---|---|
| Florida (Ambetter Health, Sunshine) | 90 calendar days from the original EOP or denial | 90 calendar days from the reconsideration denial letter | Within 60 calendar days (reconsideration is also 60) | By mail, with the Request for Reconsideration form included |
| Texas (Superior HealthPlan) | 120 days from the original EOP or denial | Within the same 120-day corrected claim/reconsideration/dispute rule | Within 60 calendar days | Portal (preferred), phone for simple rate issues, the form, or a letter |
| Kansas (Sunflower Health Plan) | 180 days from the original EOP or denial | Within the same 180-day rule | Within 30 calendar days | Portal (preferred), phone for simple rate issues, the form, or a letter |
| Member appeal (all three manuals) | 180 calendar days from Ambetter's notice of action | Then external review | Standard: 30 calendar days (FL, TX) or 15 business days (KS). Expedited: 72 hours | Written appeal to the Appeals and Grievances Department |
All three manuals are marked internally approved on June 26, 2026. Requests that arrive late are upheld as untimely unless the provider documents a qualifying circumstance. The manuals list two: a catastrophic event or administrative error, and a member who refused or was unable to show their ID card while the provider kept pursuing payment. Ambetter operates in many more states than these three. If yours isn't listed, use the provider manual on your state's Ambetter provider resources page. Don't assume a neighboring state's number applies.
The original claim filing limit is a separate clock with its own state-by-state numbers. See the timely filing section of our Ambetter appeal guide, and compare other payers in timely filing limits by insurance company.
Letter 1: Level I Request for Reconsideration (Payment or Coding Denial)
Use this letter when you think Ambetter paid the wrong amount, applied a code edit in error, or denied a service that should have been covered under your contract. It is the first-level provider appeal, and every Level II dispute has to come after one.
In Kansas and Texas, the 2026 manuals accept a written letter alone. At a minimum it must include the member's name, member ID, date of service, total charges, provider name, the original EOP and/or the original claim number, and the frequency code. The template below covers all of these fields. In Florida, a letter alone is not enough. The 2026 Florida manual says the Request for Reconsideration form must be included, and a request without it is "administratively upheld/denied as an incomplete request." Florida also limits each request to one claim.
[Practice Letterhead]

[Date]

[Ambetter plan name from the EOP, e.g., Ambetter from Superior HealthPlan]
Attn: Level I - Request for Reconsideration
PO Box 5010
Farmington, MO 63640-5010
[Confirm the address in your state's current Ambetter provider manual]

RE: Level I Request for Reconsideration
Member Name: [Member name]
Member ID: [Member ID]
Date(s) of Service: [MM/DD/YYYY]
Total Charges: $[Amount]
Original Claim Number: [Claim number] | Frequency Code: [7 or 8, if applicable]
Original EOP Date: [MM/DD/YYYY]
Provider Name / NPI / TIN: [Name] / [NPI] / [TIN]
[FLORIDA: Request for Reconsideration form attached. One claim per request.]

To the Reconsideration Team:

We request reconsideration of the claim above. The EOP dated [EOP date]
shows [paid $___ / denied] with reason code [code]: "[denial or
adjustment language, quoted exactly]."

We believe the claim was processed incorrectly because:

[Choose the one that applies and delete the others]
- Payment does not match our contracted rate. Our agreement effective
[date] sets [CPT/HCPCS code] at $[amount]; the claim paid $[amount].
- The code edit applied does not fit this encounter. [CPT] and [CPT]
were separate services, documented in the attached notes, and
modifier [__] was billed to show this.
- The service does not require prior authorization under [policy or
prior authorization list, with its date], or authorization
#[number] was obtained on [date] and is attached.

Enclosed:
1. EOP dated [date], with this claim marked
2. [Medical records. These are required for code audit, code edit and
 authorization denials, or the denial is upheld]
3. [Contract rate page, authorization approval, or policy excerpt]

Please reprocess the claim and issue a revised EOP. Contact [name] at
[phone] or [email] with any questions.

Sincerely,

[Name, Title]
[Practice Name]
[Phone] | [Fax]
Skip the blank template. Start with a review-ready draft.
Use the template as guidance, or let Muni prepare a payer-specific draft for your team to verify, sign, and submit.
First 3 appeals free, then $20 per appeal. Start with your denial letter or EOB and available records. No meeting or clearinghouse connection required.
When a phone call replaces the letter
The Kansas and Texas manuals say providers can call Provider Services for a reconsideration that needs no supporting documents, such as a claim paid at the wrong rate. The Florida manual treats that call as a payment dispute rather than a provider appeal. If the call doesn't fix the claim, send the written Level I before your state's deadline passes.
Letter 2: Reconsideration for a Timely Filing Denial
Use this letter when Ambetter denied a claim as late but you have proof the original claim arrived in time. The letter's job is to show the proof. Clearinghouse acceptance reports and payer acknowledgments carry the most weight, so put them first.
Florida's current Provider Request for Reconsideration and Claim Dispute Form has a checkbox for this exact case: "Claim was denied for untimely filing in error (attach proof of timely filing)." Get the proof together before you draft, because the letter only works if the attachment does. A clearinghouse acceptance report (999/277CA) with Ambetter's payer ID, or a portal submission confirmation, is stronger than a note in your billing system.
[Practice Letterhead]

[Date]

[Ambetter plan name from the EOP]
Attn: Level I - Request for Reconsideration
PO Box 5010
Farmington, MO 63640-5010

RE: Level I Request for Reconsideration - Timely Filing Denial Issued in Error
Member Name: [Member name]
Member ID: [Member ID]
Date(s) of Service: [MM/DD/YYYY]
Total Charges: $[Amount]
Claim Number: [Claim number]
EOP Date: [MM/DD/YYYY]
Provider Name / NPI / TIN: [Name] / [NPI] / [TIN]

To the Reconsideration Team:

The claim above was denied as untimely on the EOP dated [date]. The
claim was filed within Ambetter's [__]-day filing limit, as shown below.

Timeline:
- Date of service [or discharge date for inpatient/observation]: [date]
- Original claim submitted: [date], via [clearinghouse name / Secure
Provider Portal / paper]
- Accepted by the clearinghouse or Ambetter: [date], reference #[number]
- [If rejected and resubmitted: rejection date, reason and
resubmission date]
- Days from the start date to the first submission: [__]

Because the original submission was on time, the timely filing denial
does not apply. [If a qualifying circumstance applies instead, such as
an Ambetter administrative error or eligibility you could not have
known, describe it here and attach the documentation.]

Enclosed:
1. EOP dated [date], with this claim marked
2. Clearinghouse acceptance report (999/277CA) or portal submission
 confirmation, showing the date and Ambetter's payer ID
3. [Rejection notice and resubmission record, if applicable]

Please reprocess this claim for payment.

Sincerely,

[Name, Title]
[Practice Name]
[Phone] | [Fax]
Letter 3: Level II Claim Dispute (Cover Letter for the Dispute Form)
Use this letter only after a Level I reconsideration comes back upheld. All three 2026 manuals say a dispute filed with no reconsideration on record is treated as a reconsideration. A premature Level II doesn't skip a step. It becomes your Level I.
The dispute itself must be filed on your state's claim dispute form, filled out in full. The letter goes with the form and explains why the Level I decision was wrong. Florida's form asks for two specific attachments at Level II: the EOP with the disputed claim numbers circled, and the response to your original reconsideration. The Florida manual also expects new or additional records or supporting documents with the dispute, so don't just resend the Level I packet.
[Practice Letterhead]

[Date]

[Ambetter plan name from the EOP]
Attn: Level II - Claim Dispute
[PO Box 5010, Farmington, MO 63640-5010 (FL, TX)]
[PO Box 5000, Farmington, MO 63640-5000 (KS)]
[Confirm the address in your state's current Ambetter provider manual]

RE: Level II Claim Dispute (claim dispute form attached)
Member Name: [Member name]
Member ID: [Member ID]
Date(s) of Service: [MM/DD/YYYY]
Claim Number: [Claim number]
Original EOP Date: [MM/DD/YYYY]
Level I Reconsideration Submitted: [MM/DD/YYYY], reference #[number]
Level I Decision Letter Dated: [MM/DD/YYYY]
Provider Name / NPI / TIN: [Name] / [NPI] / [TIN]

To the Claim Dispute Team:

We dispute the Level I decision dated [date], which upheld the original
determination on the claim above. The Level I letter stated:
"[quote the rationale Ambetter gave]."

That rationale does not resolve our request because:

[Answer the Level I rationale directly. Examples:]
- The decision did not address [the contract rate / the modifier / the
authorization] raised in our Level I request.
- Ambetter's [payment policy or clinical policy, with its number and
effective date] does not apply to this service because [reason].
- New documentation, attached, shows [what it shows].

New or additional documentation enclosed:
1. Completed Ambetter claim dispute form
2. EOP(s) with the disputed claim numbers circled
3. Level I reconsideration decision letter
4. [New records, policy excerpt, contract page or authorization]

Please overturn the prior decision and reprocess the claim.

Sincerely,

[Name, Title]
[Practice Name]
[Phone] | [Fax]
Letter 4: Medical Necessity or Prior Authorization Appeal for the Member
Use this letter when Ambetter denied a service or claim as not medically necessary, or denied or never received a prior authorization. In Kansas and Texas, these denials go through the member appeal process. The provider can file for the member, but the manuals say written consent may be required.
The member appeal window is 180 calendar days from Ambetter's notice of action in all three 2026 manuals, which is longer than any of the provider reconsideration windows above. Ambetter's Texas Appeals and Grievances Guide says a member who uses a representative must complete an Appointment of Representative (AOR) form, or an equivalent written notice, signed by both the member and the representative. Get the AOR signed early, before the deadline gets close.
This letter answers a clinical decision, so write it around the criteria the denial named. Our medical necessity justification letter guide covers how to build the clinical argument in more depth.
[Practice Letterhead]

[Date]

[Ambetter plan name from the denial notice]
Attn: Appeals and Grievances Department
[Address and fax from the denial notice or your state's manual]

RE: [Standard / EXPEDITED] Appeal of Adverse Determination, filed by the
treating provider on the member's behalf
Member Name: [Member name]
Member ID: [Member ID]
Date of Birth: [MM/DD/YYYY]
Service: [Service / procedure / drug], CPT/HCPCS [code(s)]
Diagnosis: [ICD-10 code(s) and description]
Authorization or Claim Number: [Number]
Date of Notice of Action: [MM/DD/YYYY]
Treating Provider / NPI: [Name] / [NPI]
Appointment of Representative: [Signed AOR form attached / member's
written consent attached]

To the Appeals Department:

I am the treating [specialty] physician for [member name] and am
appealing, on the member's behalf, Ambetter's determination dated
[date] denying [service]. The notice states the service was denied
because "[quote the reason and any criteria cited]."

Why the criteria are met:
[Go through each criterion the notice cites. For each one, name the
record that meets it, with dates.]
- Criterion: [e.g., six weeks of conservative therapy]. Met: [physical
therapy from [date] to [date], notes attached; NSAIDs from [date]
with no improvement].
- Criterion: [e.g., imaging findings]. Met: [MRI dated [date] showing
[finding], report attached].

Clinical summary:
[Two to four sentences on the diagnosis, how severe it is, what has
been tried, and what is likely to happen if the service is delayed or
denied.]

Supporting guideline: [Specialty society guideline or published
criteria, with its title and year], which supports [service] for
patients with [condition and findings].

[EXPEDITED ONLY: Waiting for a standard decision could seriously
jeopardize the member's life, health, or ability to attain, maintain,
or regain maximum function, because [reason]. Please decide within
72 hours.]

[TEXAS ONLY: Under the Texas manual, we request that this appeal be
reviewed by a health care provider in [specialty].]

Enclosed:
1. Notice of action dated [date]
2. Signed Appointment of Representative form or member consent
3. Office notes, test results and imaging reports cited above
4. [Guideline excerpt / peer-to-peer notes, if applicable]

Sincerely,

[Physician name, credentials]
[Practice Name] | NPI [number]
[Phone] | [Fax]
Texas: asking for a same-specialty reviewer
The 2026 Texas manual says that if the provider asks, within 10 working days of the appeal request or denial, for a particular type of specialty provider to review the case, the appeal must be reviewed by a provider in the same or a similar specialty. That specialty review is completed within 15 working days. Make the request in writing and keep proof of the date you sent it. For how to prepare for a physician-to-physician conversation, see our peer-to-peer review guide.
Mistakes That Get Ambetter Appeal Letters Rejected
Most Ambetter appeals that fail on process break a filing rule rather than lose on the merits. Every item below comes from Ambetter's own 2026 manuals or current forms.
Prepare this appeal packet with your team.
Draft the appeal, coordinate missing documents, and approve the reviewed packet. Keep your clearinghouse; your practice checks deadlines and submits through the payer’s accepted channel.
First 3 appeals free, then $20 per appeal. Start with your denial letter or EOB and available records. No meeting or clearinghouse connection required.
- Skipping Level I. A dispute with no reconsideration on record is processed as a reconsideration, so you lose a level and time.
- Sending a Florida letter without the form. A Florida reconsideration without the Request for Reconsideration form is administratively upheld as incomplete.
- Leaving out records on a code audit, code edit or authorization denial. The Kansas and Texas manuals say the original denial is upheld if the records aren't received.
- Photocopied, black-and-white or handwritten claim forms. Florida's form says these are rejected up front, whatever kind of submission they're part of.
- Sending records on a USB drive or disc. The Texas Appeals and Grievances Guide says Ambetter does not accept CDs, DVDs, USB drives or flash drives.
- Filing a complaint before appealing a payment issue. The Kansas manual requires claim-payment problems to go through reconsideration and dispute before any provider complaint or grievance.
- Using a neighboring state's deadline. Level I windows range from 90 days (Florida) to 180 days (Kansas) in the 2026 manuals.
After the Internal Appeal: External Review
If Ambetter upholds a member appeal of a medical necessity or authorization denial, the member (or a provider acting as the member's representative) can ask for an independent external review. Under the federal standard on HealthCare.gov, the request must be filed within 4 months of the final denial. A standard review is decided within 45 days and an expedited review within 72 hours. Your state may run its own process if it meets the federal standards.
Ambetter's Texas guide sends external review requests to MAXIMUS Federal Services and requires the AOR form when someone files for the member. Provider payment disputes (Letters 1 through 3) are a contract matter and don't lead to this external review. The manuals point providers to the remedies in their participating provider agreement instead. For how IRO review works in practice, see our independent review organization appeal guide.
How Muni Appeals Helps With Ambetter Letters
The hard part of an Ambetter appeal is choosing the route: reconsideration, dispute or member appeal. Then the right state's deadline, address and form have to go with it. Writing the letter is the easy part.
Muni Appeals starts from the denial itself:
- Reads the uploaded EOP or notice and drafts the letter that answers the stated denial reason
- Separates payment and coding disputes from medical necessity appeals, so each letter matches its route
- Lists the attachments each route needs, such as the dispute form, marked-up EOP, records, or AOR
- Surfaces the dates staff need to verify and calendar for each level
If you're deciding between writing appeals in-house and using software, Muni Appeals Pricing Explained walks through the cost math. For the full Ambetter process beyond the letters, see our Ambetter appeal guide.
Frequently Asked Questions
What should an Ambetter appeal letter include?
At a minimum: the member's name and ID, the date of service, total charges, provider name, the original EOP date and claim number, and the frequency code if you're referencing a corrected or voided claim. These are the minimum fields the 2026 Kansas and Texas manuals list for a written reconsideration. Add the denial reason quoted exactly, a direct answer to it, and a numbered list of attachments.
How long do providers have to appeal an Ambetter denial?
It depends on the state. The 2026 manuals set 90 calendar days in Florida, 120 days in Texas and 180 days in Kansas, counted from the original EOP or denial. Florida gives another 90 days for the Level II dispute, counted from the reconsideration denial letter. For other states, check your state's current Ambetter provider manual.
Can I send an Ambetter Level II claim dispute as a letter?
Not by itself. All three 2026 manuals require the claim dispute to be filed on Ambetter's claim dispute form, completed in full. Your letter goes with the form to explain why the Level I decision was wrong.
Who appeals an Ambetter medical necessity denial, the provider or the member?
In the 2026 Kansas and Texas manuals, medical necessity and authorization denials go through the member appeal process. The provider may file it for the member, and written consent may be required. The member has 180 calendar days from Ambetter's notice of action. Florida's manual also allows a Level I reconsideration for these denials if medical records are attached.
Where do I mail an Ambetter reconsideration?
The 2026 Kansas, Florida and Texas manuals send Level I reconsiderations to PO Box 5010, Farmington, MO 63640-5010. Level II disputes go to PO Box 5010 in Florida and Texas, and to PO Box 5000 in Kansas. Kansas and Texas call the Secure Provider Portal the preferred way to submit. Always confirm the address against your state's current manual or your EOP.
How long does Ambetter take to decide an appeal?
Under the 2026 manuals, Level II claim disputes are resolved within 60 calendar days in Florida and Texas and within 30 in Kansas. Florida also resolves Level I reconsiderations within 60 days. Member appeals are decided within 30 calendar days in Florida and Texas, or 15 business days in Kansas, and expedited appeals within 72 hours.
Pick the Route First, Then the Letter
A strong argument sent down the wrong Ambetter route fails. So does a letter mailed without the form your state requires. Check three things before you draft: the denial reason, your state's manual, and whether you're past Level I. Then choose the letter that matches.
This guide reflects the 2026 Ambetter provider manuals for Kansas, Florida and Texas (each internally approved June 26, 2026), Ambetter's current Florida claim dispute form, and Ambetter's Texas Appeals and Grievances Guide, as reviewed September 25, 2026. Deadlines, addresses, routing and resolution times vary by state and product and can change. Confirm them in your state's current Ambetter provider manual, your participating provider agreement, and the denial notice before filing. This information is for administrative and billing purposes and is not legal or medical advice.