

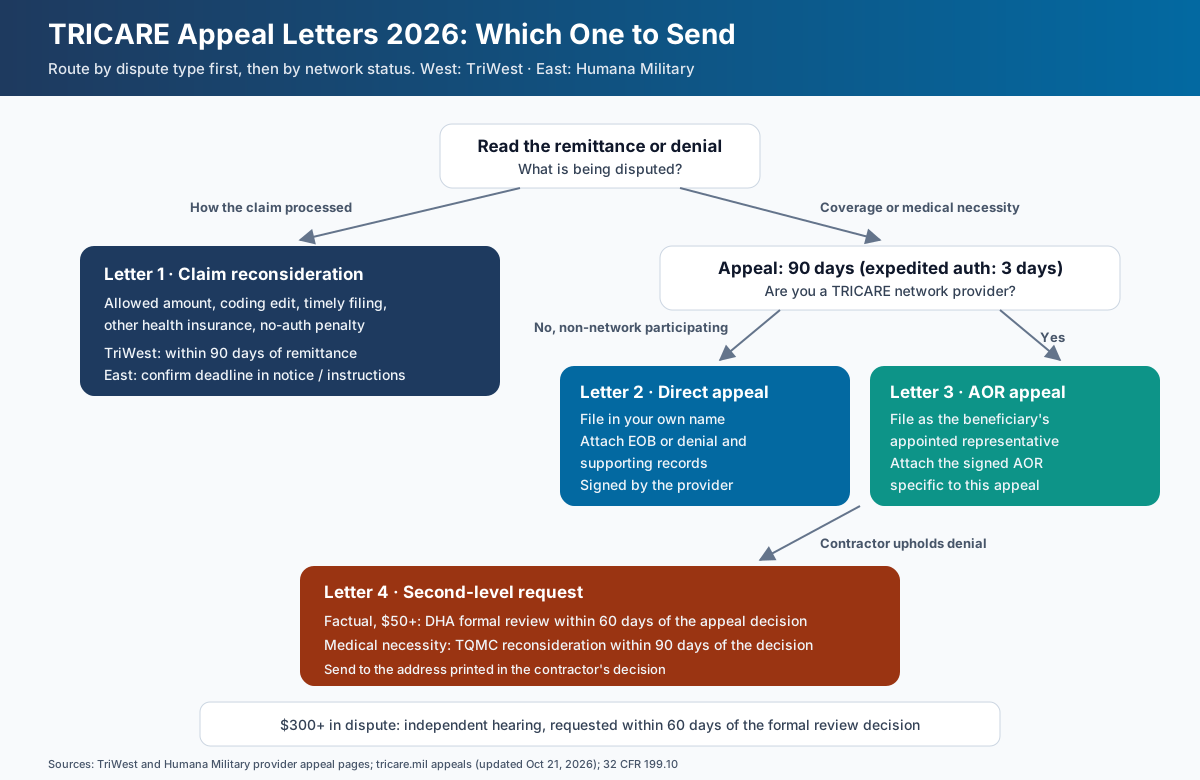
Which TRICARE letter you send depends on the dispute and on your network status. A dispute over how a claim processed (allowed amount, timely filing, other health insurance, a no-authorization penalty) is a reconsideration. A denial as not medically necessary or as a policy limitation is an appeal. TriWest claim reconsiderations must arrive within 90 days of the remittance date; routine appeals have a 90-day decision-date window (TriWest; TRICARE). For East allowable-charge reviews, confirm the deadline in your notice and Humana Military's current instructions. A non-network participating provider can appeal in its own name. A network provider can't: it needs a signed Appointment of Representative (AOR) from the beneficiary, specific to that appeal (Humana Military). The four templates below cover each case.
Why One Generic TRICARE Appeal Letter Isn't Enough
A single all-purpose letter fails on TRICARE because the program checks three things before it reviews your argument: whether the issue is a reconsideration or an appeal, whether you're allowed to file it, and which level you're at. Commercial templates skip all three, since most commercial plans let any treating provider appeal.
TRICARE appeals run under 32 CFR 199.10. Under that rule, a request has to be in writing, state the specific matter in dispute, and include a copy of the initial determination. The same section says a nonparticipating provider is not a party to the initial determination and may not appeal. The regional contractors add a further rule on top: network providers aren't appropriate appealing parties unless the beneficiary appoints them in writing.
For the full two-track process (factual vs. medical necessity, the $50 and $300 escalation thresholds, and the Point-of-Service trap), see the TRICARE appeal guide for providers. This post is the letter set: which one to send, and the exact language for each.
Step 1: Decide Whether It's a Reconsideration or an Appeal
If you're disputing how a claim was processed, send a reconsideration. If you're disputing a coverage or medical necessity decision, send an appeal. TriWest's provider page draws that line explicitly, and Humana Military separates "allowable charge reviews" from medical necessity appeals the same way.
| What the remittance or denial says | Request type | Letter to use |
|---|---|---|
| Allowed amount, coding edit, other health insurance (OHI), timely filing denial, no-authorization penalty | Claim reconsideration (East: allowable charge review) | Letter 1 |
| Denied as not medically necessary, or as a TRICARE policy limitation (non-covered) | Appeal: medical necessity or factual | Letter 2 (non-network participating) or Letter 3 (network) |
| Processed as Point-of-Service, and the service was emergency care | Appeal | Letter 2 or Letter 3 |
| Prior authorization or referral denied | Authorization appeal (routine 90 days, expedited 3 days) | Letter 2 or Letter 3, marked expedited if urgent |
| Contractor upheld your appeal | Second level: DHA formal review (factual) or TQMC reconsideration (medical necessity) | Letter 4 |
| Claim denied for missing medical records | Records submission, not an appeal | Records cover sheet to the address on the denial |
Sources: TriWest reconsiderations and appeals; Humana Military appeals and reconsideration; TRICARE West authorization appeals (updated March 19, 2026).
For the general version of this fork outside TRICARE, see reconsideration vs. appeal.
Step 2: Confirm You Can File the Appeal Yourself
Non-network participating providers can file appeals in their own name. Network providers need a signed AOR from the beneficiary, and non-participating providers can't appeal at all. This is where most TRICARE provider appeals stall. A letter from a network practice with no AOR attached is treated as filed by someone who isn't an appropriate appealing party, so the clock keeps running while nothing is reviewed.
| Your status | Can you appeal in your own name? | What to attach |
|---|---|---|
| Non-network participating provider | Yes. Humana Military notes it can't submit an expedited appeal. | EOB or remittance, supporting records |
| TRICARE network provider | No. File as the beneficiary's appointed representative. | Signed AOR specific to this appeal, plus EOB and records |
| Non-participating provider | No. Not a party to the determination under 32 CFR 199.10. | Beneficiary files, or appoints a representative |
Humana Military's appeal page says "network providers cannot appeal without an AOR specific to the appeal being requested" (Humana Military). The West Region page says the same thing: "Network participating providers can't file an appeal without a signed Authorization of Representative form" (TRICARE West). TriWest's form is titled Appointment of Representative and Authorization to Disclose Information, and it asks for the denied authorization or claim numbers along with the beneficiary's signature. Use your region's current form.
Reconsiderations Are Different
These standing rules apply to appeals. A claim reconsideration is a provider request about how the claim processed. TriWest accepts provider reconsiderations directly, and Humana Military limits its "claims reconsideration (medical review)" lane to participating providers. You don't need an AOR to dispute an allowed amount or a timely filing denial.
Where to Send Each Letter
Reconsiderations and appeals go to different addresses in both regions, so match the address to the letter. These are the destinations published on the contractors' pages as of October 2026. If the denial letter lists a different address, use the denial letter.
| Letter | TRICARE West (TriWest) | TRICARE East (Humana Military) |
|---|---|---|
| Letter 1: Claim reconsideration / allowable charge review | TRICARE West Correspondence, P.O. Box 2748, Virginia Beach, VA 23450 · Fax 1-866-852-1969 | Customer Service, Humana Military, PO Box 202146, Florence, SC 29502-2146 · Fax (877) 489-0011 |
| Letters 2–3: Claim appeal | TRICARE West Claims Appeals, P.O. Box 2777, Virginia Beach, VA 23450 · Fax 1-866-670-4330 | Humana Military Appeals, PO Box 740044, Louisville, KY 40201-7444 · Fax (877) 850-1046 · humanamilitary.com/appeal (preferred) |
| Letters 2–3: Authorization appeal | TriWest Appeals and Reconsideration Department, P.O. Box 2636, Virginia Beach, VA 23450 · Fax 866-852-1919 | Same as claim appeal |
| Letter 4: Second level | Address printed in the contractor's appeal decision | Address printed in the contractor's appeal decision |
Sources: TriWest, TRICARE West authorization appeals, Humana Military, TRICARE East appeals (updated March 19, 2026).
Letter 1: Claim Reconsideration Request
Use this letter when the claim paid wrong or denied for a processing reason: allowed amount, timely filing, OHI, a coding edit, or a no-authorization penalty. TriWest requires that it arrive no later than 90 days from the remittance date. Include whatever proves the processing error, such as a clearinghouse acceptance report for a timely filing denial or the primary EOB for an OHI issue.
[Practice Letterhead]
[Date]

[TRICARE West Correspondence, P.O. Box 2748, Virginia Beach, VA 23450]
— or —
[Customer Service, Humana Military, PO Box 202146, Florence, SC 29502-2146]

RE: Provider Claim Reconsideration Request
Beneficiary: [Name] | DOB: [MM/DD/YYYY]
Sponsor DoD Benefits Number (or SSN, last 4): [Number]
Claim Number: [Number] | Date(s) of Service: [Dates]
Remittance/EOB Date: [MM/DD/YYYY]
Billed: $[Amount] | Allowed: $[Amount] | Paid: $[Amount]
Provider: [Name], NPI [Number], TIN [Number]

ISSUE IN DISPUTE
We request reconsideration of the processing of this claim. The
remittance shows [quote the denial or adjustment code and its
description]. We believe this is a processing error because:

[Select and complete one]
[ ] Timely filing: the original claim was received on [date], within
    the filing limit. Clearinghouse acceptance report enclosed.
[ ] Other health insurance: [primary payer] processed on [date];
    primary EOB enclosed. / The beneficiary has no other coverage;
    updated OHI information enclosed.
[ ] Allowed amount: CPT/HCPCS [code] was allowed at $[amount]. Under
    [the applicable TRICARE reimbursement methodology or our network
    agreement, section __], the allowed amount should be $[amount].
[ ] Authorization penalty: authorization [number] was approved for
    [dates/services] before the service date. Approval enclosed.
[ ] Coding edit: [explain why the edit was applied in error and cite
    the supporting documentation].

REQUESTED ACTION
Please reprocess the claim and issue corrected payment of $[amount].

ENCLOSURES
1. Copy of remittance/EOB dated [date]
2. [Proof of timely filing / primary EOB / authorization approval /
   fee schedule excerpt / medical records]

For TriWest: this request is submitted within 90 days of the remittance date.
For Humana Military: applicable review deadline and source: [Confirm from
the notice and current contractor instructions before sending].
Delete the line that does not apply.

Sincerely,

[Name, Title]
[Practice Name] | Phone: [Number] | Fax: [Number]
Skip the blank template. Start with a review-ready draft.
Use the template as guidance, or let Muni prepare a payer-specific draft for your team to verify, sign, and submit.
First 3 appeals free, then $20 per appeal. Start with your denial letter or EOB and available records. No meeting or clearinghouse connection required.
Letter 2: Appeal From a Non-Network Participating Provider
Use this letter when you're a non-network participating provider and the claim or authorization was denied as not medically necessary, as a policy limitation, or as POS-only for emergency care. The appeal has to be written, signed, state the issue in dispute, and include the initial denial and supporting documents (TriWest). If records are still being gathered, send the letter on time and say more documents will follow, as TRICARE advises.
[Practice Letterhead]
[Date]

[TRICARE West Claims Appeals, P.O. Box 2777, Virginia Beach, VA 23450]
[TriWest Appeals and Reconsideration Dept., P.O. Box 2636,
Virginia Beach, VA 23450 — authorization appeals]
— or —
[Humana Military Appeals, PO Box 740044, Louisville, KY 40201-7444]

RE: Appeal of [Claim / Authorization] Denial
Appealing Party: [Provider Name], non-network participating provider
Beneficiary: [Name] | DOB: [MM/DD/YYYY]
Sponsor DoD Benefits Number (or SSN, last 4): [Number]
[Claim / Authorization] Number: [Number]
Date(s) of Service or Requested Service: [Dates]
Date of Denial / EOB: [MM/DD/YYYY]

APPEAL TYPE
[ ] Medical necessity: care denied as not medically necessary
[ ] Factual: denied as a TRICARE policy limitation / non-covered
[ ] Point-of-Service: processed as POS-only; services were emergency
    care

ISSUE IN DISPUTE
The [EOB / denial letter] states: "[quote the exact denial reason]."
We dispute this determination for the reasons below.

BASIS FOR APPEAL
[Medical necessity: summarize the diagnosis (ICD-10 [code]), the
service (CPT/HCPCS [code]), prior treatments tried and their results,
and why this service is required now. Address each criterion the
denial cited and attach the records that meet it.]

[Factual: identify the TRICARE policy provision the denial relied on
and explain why the service falls within coverage, citing the
applicable TRICARE Policy Manual section or benefit description.]

[POS emergency: describe the presenting symptoms and why the visit
was emergency care rather than a non-referred routine visit; attach
the ED or triage record.]

REQUESTED ACTION
Please reverse the denial and [approve authorization / reprocess the
claim for payment].

ENCLOSURES
1. Copy of the EOB / denial letter dated [date]
2. Letter of medical necessity from [Treating Provider, Credentials]
3. Relevant chart notes, test results, and treatment history
4. [Clinical guideline or literature excerpt, if cited]
[Additional records will follow under separate cover.]

This appeal is submitted within 90 days of the date of the denial.

Signature of appealing party:

______________________________
[Provider Name, Credentials] | NPI: [Number]
[Practice Name] | Phone: [Number] | Fax: [Number]
Letter 3: Appeal From a Network Provider With an Appointment of Representative
If you're a TRICARE network provider, file the appeal on the beneficiary's behalf as their appointed representative, and attach the signed AOR. Without the AOR, the contractor can refuse to treat the letter as an appeal. Get the form signed as soon as the denial arrives so the 90-day window isn't spent chasing a signature.
[Practice Letterhead]
[Date]

[TRICARE West Claims Appeals, P.O. Box 2777, Virginia Beach, VA 23450]
[TriWest Appeals and Reconsideration Dept., P.O. Box 2636,
Virginia Beach, VA 23450 — authorization appeals]
— or —
[Humana Military Appeals, PO Box 740044, Louisville, KY 40201-7444]

RE: Appeal Filed by Appointed Representative
Appealing Party: [Beneficiary Name]
Representative: [Provider/Practice Name], TRICARE network provider
Beneficiary DOB: [MM/DD/YYYY]
Sponsor DoD Benefits Number (or SSN, last 4): [Number]
[Claim / Authorization] Number: [Number]
Date(s) of Service or Requested Service: [Dates]
Date of Denial / EOB: [MM/DD/YYYY]

REPRESENTATION
[Beneficiary Name] has appointed [Provider/Practice Name] as their
representative for this appeal. The signed Appointment of
Representative and Authorization to Disclose Information form, which
lists the [claim / authorization] number above, is enclosed.

APPEAL TYPE
[ ] Medical necessity   [ ] Factual / policy limitation
[ ] Expedited: delay could seriously jeopardize the beneficiary's
    life or health (authorization or continued inpatient stay only)

ISSUE IN DISPUTE
The [EOB / denial letter] states: "[quote the exact denial reason]."
On behalf of the beneficiary, we dispute this determination.

BASIS FOR APPEAL
[Same structure as a direct appeal: diagnosis and ICD-10 code, service
and CPT/HCPCS code, treatment history, and a point-by-point response to
each criterion the denial cited.]

REQUESTED ACTION
Please reverse the denial and [approve authorization / reprocess the
claim for payment].

ENCLOSURES
1. Signed Appointment of Representative form (specific to this
   appeal)
2. Copy of the EOB / denial letter dated [date]
3. Letter of medical necessity and supporting clinical records

This appeal is submitted within [90 days / 3 calendar days for an
expedited authorization appeal] of the denial.

Signature of representative:

______________________________
[Provider Name, Credentials] | NPI: [Number]
[Practice Name] | Phone: [Number] | Fax: [Number]
Expedited Appeals Have a 3-Day Window
Expedited appeals cover only pre-authorization of services and the continuation of inpatient stays (TRICARE). They must be filed within three calendar days of receiving the denial (TRICARE West). Fax or use the portal; don't mail an expedited request.
Letter 4: Second-Level Request (DHA Formal Review or TQMC Reconsideration)
If the contractor upholds the denial, the next step depends on the track. For a factual denial with $50 or more in dispute, request a Defense Health Agency formal review, postmarked within 60 days of the appeal decision. For a medical necessity denial, request reconsideration from the TRICARE Quality Monitoring Contractor (TQMC), postmarked within 90 days of the appeal decision (TRICARE). Send it to the address printed in the contractor's decision. The same standing rules apply here, so a network provider still needs the AOR.
Prepare this appeal packet with your team.
Draft the appeal, coordinate missing documents, and approve the reviewed packet. Keep your clearinghouse; your practice checks deadlines and submits through the payer’s accepted channel.
First 3 appeals free, then $20 per appeal. Start with your denial letter or EOB and available records. No meeting or clearinghouse connection required.
[Practice Letterhead]
[Date]

[Address exactly as printed in the contractor's appeal decision]

RE: Request for [Formal Review / Reconsideration]
[ ] Formal review: factual determination, amount in dispute $50+
[ ] Reconsideration: medical necessity determination (TQMC)
Appealing Party: [Provider Name / Beneficiary Name]
[Representative: Provider/Practice Name, if filing under an AOR]
Beneficiary: [Name] | DOB: [MM/DD/YYYY]
Sponsor DoD Benefits Number (or SSN, last 4): [Number]
[Claim / Authorization] Number: [Number]
Contractor Appeal Decision Date: [MM/DD/YYYY]
Amount in Dispute: $[Amount]

REQUEST
We request [formal review / reconsideration] of the enclosed appeal
decision issued by [TriWest Healthcare Alliance / Humana Military] on
[date], which upheld the denial of [service, CPT/HCPCS code].

WHY THE APPEAL DECISION IS INCORRECT
1. The decision states: "[quote its rationale]."
2. [Explain the specific error: a criterion misapplied, records
   overlooked, or the wrong policy provision cited.]
3. [Identify any new evidence enclosed that was not available at the
   first level, and explain what it shows.]

ENCLOSURES
1. Copy of the contractor's appeal decision dated [date]
2. Copy of the original denial and the first-level appeal
3. [New or additional clinical documentation]
4. [Signed Appointment of Representative form, if applicable]

This request is submitted within [60 days (formal review) / 90 days
(reconsideration)] of the date on the appeal decision.

Sincerely,

[Provider Name, Credentials] | NPI: [Number]
[Practice Name] | Phone: [Number] | Fax: [Number]
After formal review or TQMC reconsideration, disputes of $300 or more can go to an independent hearing. Request it within 60 days of the formal review decision. The hearing officer issues a recommended decision, and the DHA director (or a designee) or the Assistant Secretary of Defense for Health Affairs makes the final call (TRICARE). Below $300, the second-level decision is final.
Deadlines Every TRICARE Letter Has to Meet
Count from the date on the remittance, EOB, or decision letter, and mail with a postmark you can prove. Under 32 CFR 199.10, a request is deemed filed on the date it's mailed and postmarked, or on the date received if there's no postmark. The contractors' own pages phrase some of these clocks as "received," so leave margin.
| Request | Deadline | Counted from |
|---|---|---|
| Claim reconsideration (TriWest) | No later than 90 days | Remittance date |
| Claim or authorization appeal | 90 days | Date on the EOB, remittance, or denial |
| Expedited authorization appeal | 3 calendar days | Receipt of the denial letter |
| DHA formal review (factual, $50+) | 60 days | Date on the contractor's appeal decision |
| TQMC reconsideration (medical necessity) | 90 days | Date on the contractor's appeal decision |
| Independent hearing ($300+) | 60 days | Date of the formal review decision |
Sources: TRICARE appeals (updated October 21, 2026); TriWest; TRICARE West authorization appeals. For how these compare with commercial and Medicare clocks, see insurance appeal deadlines.
Mistakes That Get TRICARE Letters Rejected or Delayed
Most rejected TRICARE letters fail on routing or standing, not on the clinical argument.
- No AOR on a network-provider appeal. The contractor can treat it as filed by an improper party. Have the AOR signed at intake.
- Appealing a processing dispute. Allowed-amount, OHI, and timely filing issues go to the reconsideration address, not the appeals box.
- Using the old region map. Since January 1, 2025, TriWest has handled the West Region, including Arkansas, Illinois, Louisiana, Oklahoma, Texas, and Wisconsin. Route by the beneficiary's region, not your practice address. The TRICARE appeal guide covers the realignment.
- Appealing a POS cost-share that wasn't emergency care. Most Point-of-Service determinations aren't appealable. A missing referral is fixed with a referral.
- Waiting for complete records. Send the letter inside the window and say more documentation will follow.
- Treating a medical-records denial as an appeal. TriWest sends those to a separate records address with its own cover sheet.
If a claim seems stalled rather than denied, confirm its status first. The appeal status call script works for contractor calls too.
How Muni Appeals Helps With TRICARE Letters
Muni Appeals helps staff organize an uploaded denial and supporting evidence, research the appeal, and prepare a draft for review. For TRICARE, staff must determine whether to request reconsideration or appeal, select the contractor and submission channel, confirm standing and any AOR requirement, and verify the controlling deadline against the notice and current contractor instructions. Staff review the draft, attach the required records, and submit it through the contractor's channel.
For the clinical core of Letters 2 through 4, use the medical necessity justification letter guide. Practices that also see VA Community Care patients can compare the VA Community Care appeal guide, where TriWest is also a contractor but the reconsideration rules differ.
Frequently Asked Questions
Can a TRICARE network provider file an appeal?
Not in its own name. Humana Military and the TRICARE West Region both state that network providers can't appeal without a signed Appointment of Representative form from the beneficiary. With the AOR attached, the network provider files as the beneficiary's representative.
What is the difference between a TRICARE reconsideration and an appeal?
A reconsideration disputes how a processed claim paid, for example an allowed amount, a timely filing denial, other health insurance, or a no-authorization penalty. An appeal disputes a denial as not medically necessary, a policy limitation, or a POS-only determination for emergency care. They go to different addresses in both regions.
How long do I have to send a TRICARE appeal letter?
Ninety days from the date on the EOB, remittance, or denial for routine claim and authorization appeals, and three calendar days for an expedited authorization appeal. Second-level requests are due within 60 days (DHA formal review) or 90 days (TQMC reconsideration) of the contractor's appeal decision.
Can a non-participating provider appeal a TRICARE denial?
No. Under 32 CFR 199.10, a nonparticipating provider is not a party to the initial determination and may not appeal. The beneficiary can appeal or appoint a representative.
Where do I send a TRICARE East appeal letter?
Humana Military Appeals, PO Box 740044, Louisville, KY 40201-7444, fax (877) 850-1046, or online at humanamilitary.com/appeal, which Humana Military lists as the preferred method. Allowable charge reviews go to Humana Military Customer Service, PO Box 202146, Florence, SC 29502-2146.
Where do I send a TRICARE West appeal letter?
Claim appeals go to TRICARE West Claims Appeals, P.O. Box 2777, Virginia Beach, VA 23450 (fax 1-866-670-4330). Authorization appeals go to TriWest's Appeals and Reconsideration Department, P.O. Box 2636, Virginia Beach, VA 23450 (fax 866-852-1919). Reconsiderations go to TRICARE West Correspondence, P.O. Box 2748.
What should a TRICARE appeal letter include?
It must be in writing and signed by the appealing party or its representative. It should state the specific issue in dispute and include a copy of the initial denial (EOB or remittance) plus supporting documentation. Network providers also need the signed AOR.
Send the Right TRICARE Letter the First Time
On TRICARE, the letter that wins is usually the one that went to the right box, from a party allowed to send it, inside the right window. Match the request type first, check network status second, and then make the clinical case.
Muni Appeals helps practices:
- Organize uploaded denials and supporting evidence
- Research and draft appeal arguments for staff review
- Prepare a draft that staff check against the contractor's current requirements
These templates reflect TRICARE West Region (TriWest Healthcare Alliance) and East Region (Humana Military) procedures published as of October 2026. Addresses, forms, and contractor procedures change. Confirm current instructions on your denial letter and the contractor's website before filing. This information is for administrative and billing purposes and is not legal or medical advice.